



To evaluate the impact of therapy optimization on medication-related safety in patients with liver cirrhosis.
MethodSystematic review of clinical trials and before-and-after studies with time series analysis in CENTRAL, MEDLINE, and INAHTA databases. The certainty of the evidence was assessed using the GRADE approach, and the risk of bias was evaluated with the ROBUST-RCT tool.
ResultsSix articles were identified, all corresponding to a single randomized controlled trial (116 patients) that evaluated the effectiveness of a pharmacist-led intervention (medication reconciliation and individualized health education) compared to usual care. Although no significant differences were found in all-cause mortality or the crude relative risk of hospitalization, the adjusted incidence rate analysis revealed that the intervention significantly reduced unplanned hospitalizations by 48%. Furthermore, within the intervention group, each unit increase in the rate of high-risk medication-related problems was associated with more than three-fold higher odds of mortality, independently of disease severity.
ConclusionsThere is a current scarcity of high-quality studies in this field. Nevertheless, the available evidence suggests that pharmaceutical follow-up is an effective strategy to reduce preventable hospitalizations in outpatients with decompensated cirrhosis. Pharmacological safety is vital for survival, justifying the integration of the pharmacist into the clinical team.
identificar la evidencia disponible sobre el impacto de la adecuación del tratamiento en la seguridad relacionada con el uso de medicamentos en pacientes con cirrosis hepática.
Métodose realizó una revisión sistemática de ensayos clínicos y estudios antes-después con análisis de series temporales en CENTRAL, MEDLINE e INAHTA. La certeza de la evidencia se evaluó mediante GRADE y el riesgo de sesgo con ROBUST-RCT.
Resultadosse encontraron 6 artículos pertenecientes a un único ensayo clínico aleatorizado (116 pacientes) que evaluaba la eficacia de una intervención farmacéutica (conciliación y educación sanitaria individualizada) frente al cuidado habitual. Aunque no hubo diferencias significativas en la mortalidad global ni en el riesgo relativo bruto de hospitalización, el análisis ajustado por la tasa de incidencia reveló que la intervención redujo significativamente las hospitalizaciones no programadas en un 48%. Asimismo, en el grupo intervención, cada incremento en la tasa de problemas relacionados con los medicamentos de alto riesgo multiplicó por más de 3 las probabilidades de mortalidad, independientemente de la gravedad de la enfermedad.
Conclusionesexiste una escasez de estudios de alta calidad en este ámbito. No obstante, la evidencia disponible sugiere que el seguimiento farmacéutico es una estrategia eficaz para reducir las hospitalizaciones prevenibles en pacientes ambulatorios con cirrosis descompensada. La seguridad farmacológica es vital para la supervivencia, lo que justifica la inclusión del farmacéutico en el equipo clínico.
Liver cirrhosis (LC) induces pharmacokinetic and pharmacodynamic alterations that increase susceptibility to adverse drug reactions (ADRs). Patients with LC take an average of nine medications daily1 and frequently experience medication-related problems (MRPs). Selecting the appropriate medication and optimizing dose adjustment are essential to prevent medication-related problems.1,2 Interventions involving medication reviews are effective in minimizing the use of medications, preventing MRPs and improving health outcomes.3 However, there is a scarcity of data regarding medication safety in LC patients, with healthcare professionals having shown a low level of knowledge of this clinical setting.4,5 Limited evidence is currently available regarding the potential benefits of medication optimization in patients with LC, underscoring the need for further investigation and the development of patient-centered pharmaceutical interventions.
The objective of this study was to identify the available evidence on the impact of medication optimization on medication safety in LC patients.
MethodsA systematic review was conducted in accordance with Cochrane rapid review guidelines. Results are provided based on the PRISMA flow diagram. The Study Protocol was registered with PROSPERO (CRD420251082246).
To maximize the statistical power of the study and ensure the reliability of results, the search was restricted to placebo-controlled clinical trials and pre-post testing studies with time series analysis. Observational studies were excluded due to their higher susceptibility to bias. Search included studies in adult patients with LC assessing the effectiveness of pharmaceutical interventions (medication review, conciliation, deprescribing or optimization) available either in English, Spanish or French by July 3 2025.
The research question was formulated in accordance with the PICO instrument: Is medication review effective in reducing the incidence of adverse drug reactions, medication-related problems, hospital admissions, mortality, and decompensated cirrhosis or in improving health-related quality of life in patients with liver cirrhosis? (Appendix 1). A literature search was carried out on MEDLINE, CENTRAL and INAHTA (Appendix 2). Two reviewers independently screened titles and abstracts, followed by full-text assessment of potentially eligible studies. Any disagreements were resolved by a third reviewer. Record screening was carried out using the Covidence tool. Data were extracted by one reviewer and independently checked for accuracy by a second reviewer.
Results were presented through narrative synthesis, estimating relative risk (RR) for dichotomous variables and incidence rate ratios (IRRs) for recurrent events. Multivariable logistic regression analysis was performed to identify predictors of mortality and estimate their adjusted odds ratios (ORs). Risk of bias was assessed using the ROBUST-RCT instrument, evaluated by one reviewer and independently verified by a second reviewer.
Outcome prioritization was performed by a multidisciplinary team composed of five clinical pharmacists and two physicians (a general practitioner and a hepatologist) using the GRADE tool.
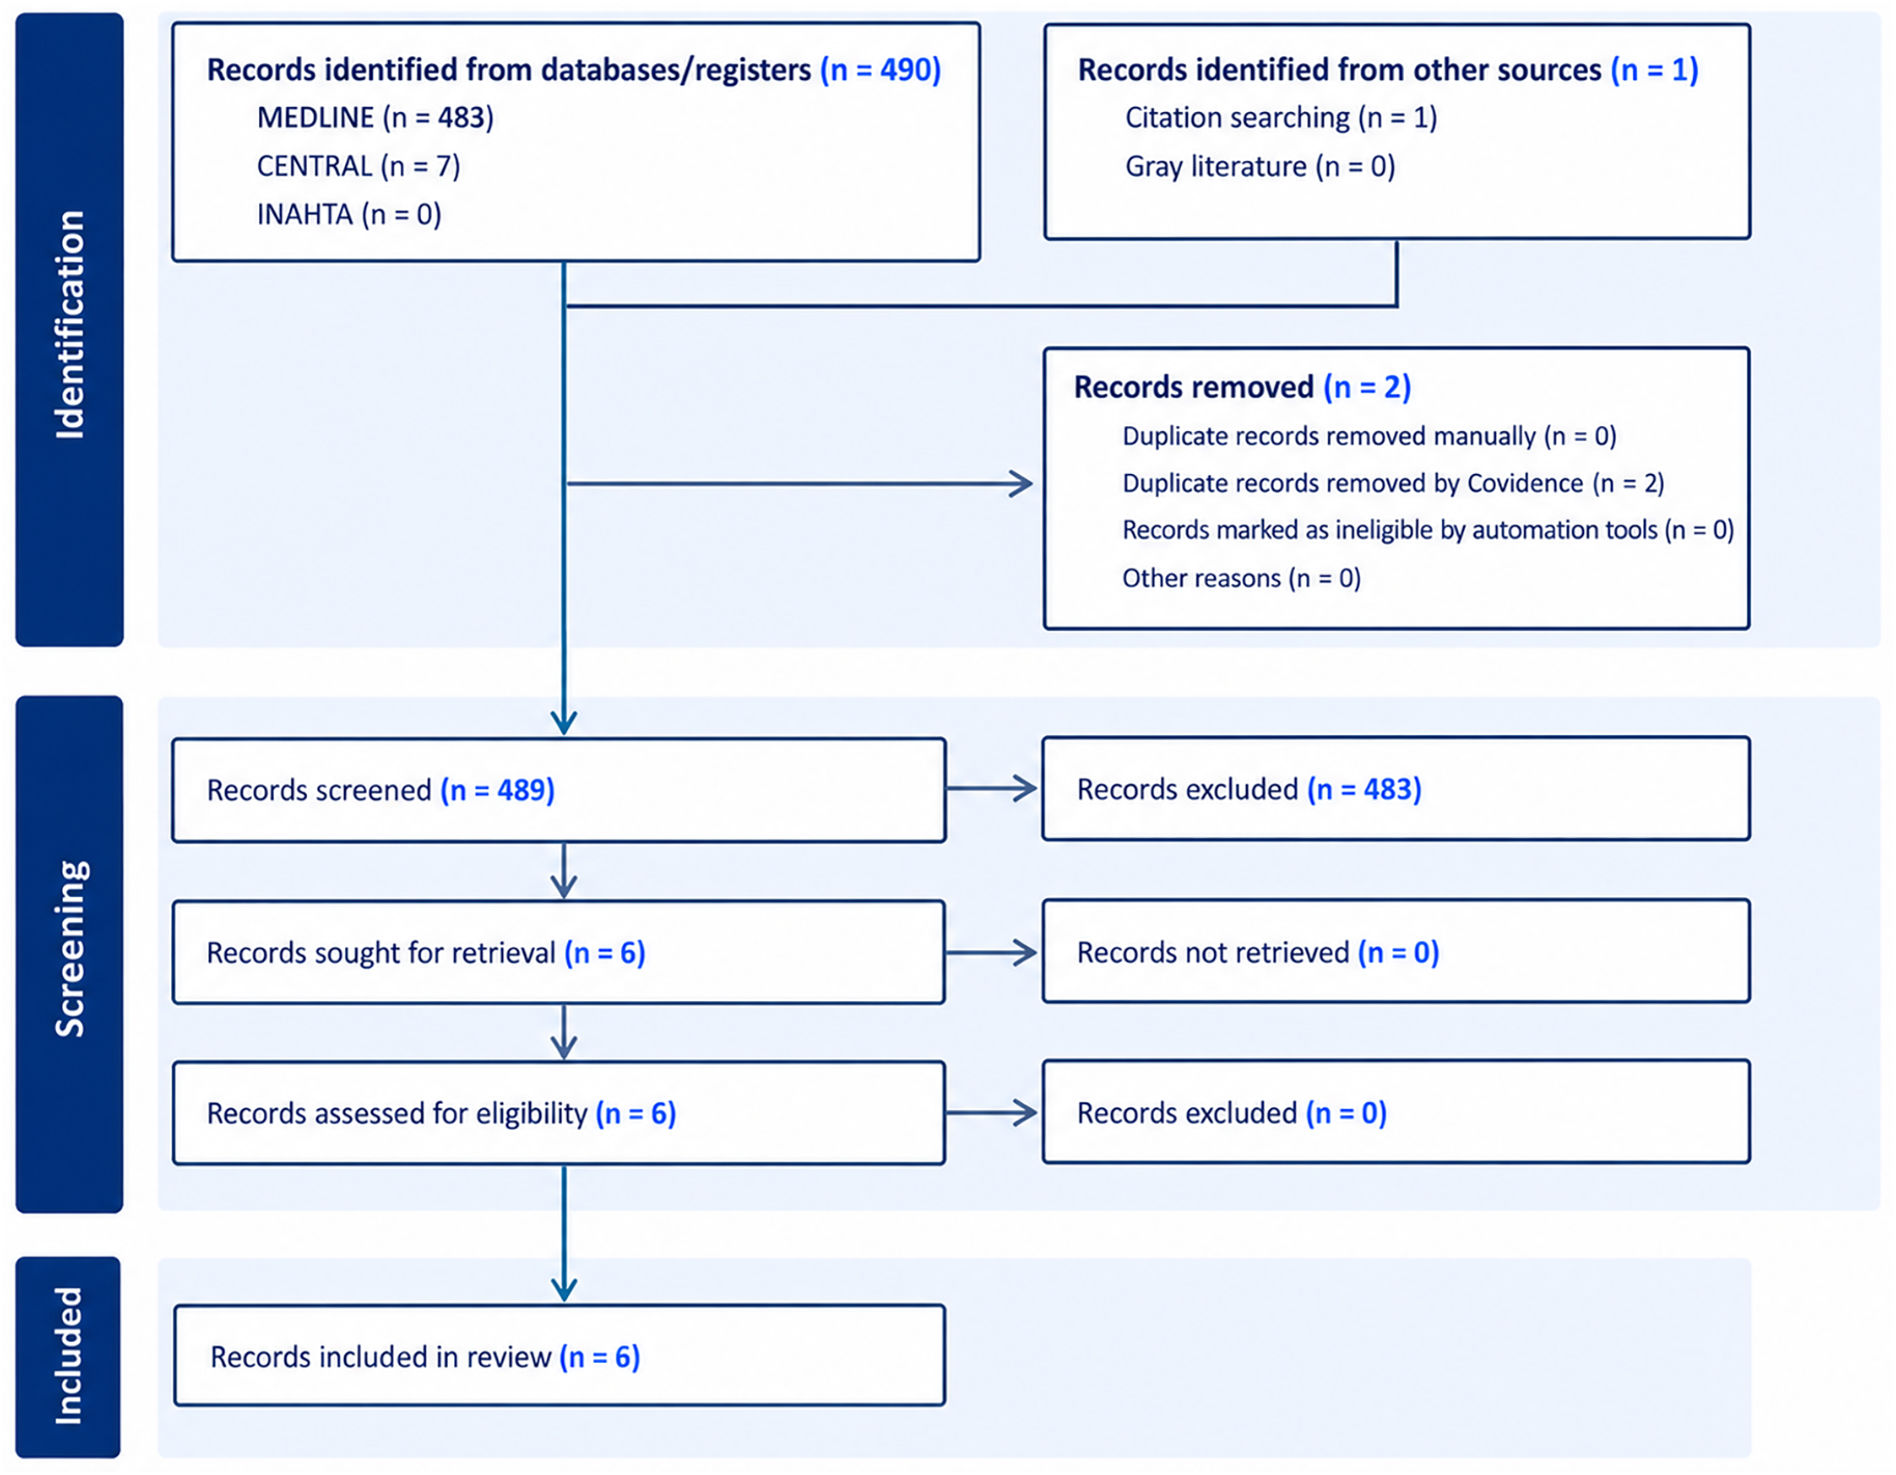
ResultsA total of six papers were selected for full-text reading, all related to a single clinical trial, which was finally included for analysis.6–11Fig. 1 contains a PRISMA flow diagram mapping out the record screening process. Most of the studies found in the search were excluded because they involved biliary cirrhosis, pediatric patients, or did not meet the required study design. A total of 116 patients (57 in the intervention arm, 59 in the control arm), with matched clinical and demographic characteristics, were included.10 The study evaluated a pharmacological intervention implemented in outpatients with decompensated LC. Patients were randomized to receive either the standard of care (follow-up consultations with the hepatologist) or the intervention (four consultations with the hospital pharmacist, who performed medication reconciliation and delivered health education to improve patients’ self-management and knowledge of their disease).

The risk of bias for mortality and hospital admissions was scored as low (Appendix 3), since the nature of the study hindered a double- or single-blind study design.
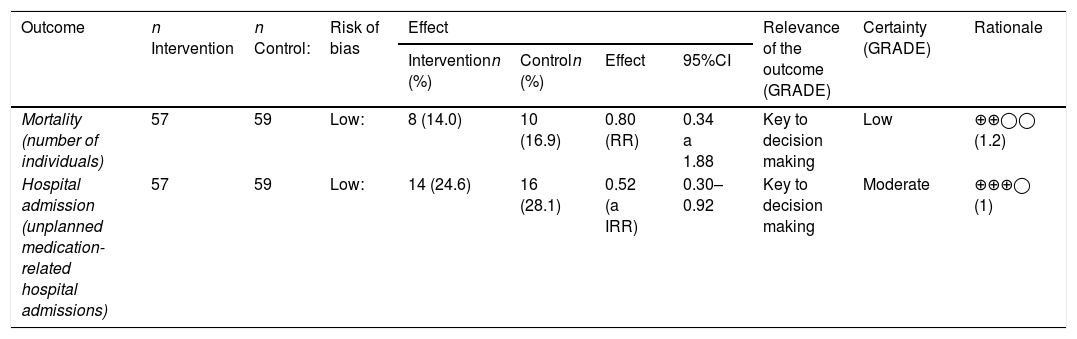
A total of 51 unplanned medication-related hospital admissions were identified, with 64.7% having been identified as avoidable. Although no differences were observed in the unadjusted analysis, the multivariable-adjusted model–including Child-Pugh score–therapeutic burden, and previous history of varicose vein bleeding as covariates, showed that the pharmaceutical intervention significantly reduced the incidence of hospital admissions by 48% (IRR 0.52; 95% CI: 0.30–0.92; p = 0.025)6,10 (Table 1). Likewise, the incidence of high-risk MRPs was found to be 2.5 times higher among the patients who needed hospital admission, as compared to outpatients (IRR 2.48; p = 0.006).10
Results of the clinical trial assessing outcomes associated with “mortality” and “hospital admissions”.
| Outcome | n Intervention | n Control: | Risk of bias | Effect | Relevance of the outcome (GRADE) | Certainty (GRADE) | Rationale | |||
|---|---|---|---|---|---|---|---|---|---|---|
| Interventionn (%) | Controln (%) | Effect | 95%CI | |||||||
| Mortality (number of individuals) | 57 | 59 | Low: | 8 (14.0) | 10 (16.9) | 0.80 (RR) | 0.34 a 1.88 | Key to decision making | Low | ⊕⊕◯◯ (1.2) |
| Hospital admission (unplanned medication-related hospital admissions) | 57 | 59 | Low: | 14 (24.6) | 16 (28.1) | 0.52 (a IRR) | 0.30–0.92 | Key to decision making | Moderate | ⊕⊕⊕◯ (1) |
95% CI: 95% confidence interval; IRR: incidence rate ratio; RR: relative risk. Admission outcomes are presented as the adjusted incidence rate ratio (aIRR) as estimated using a multivariable model including Child-Pugh score, number of baseline medications, history of varicose vein bleeding, and alcoholic etiology.
(i) The level of certainty was downgraded by one level due to evidence having been provided by a single clinical trial with a small sample size.
(ii) The certainty of evidence for mortality was downgraded by two levels due to serious imprecision; the confidence interval crossed the thresholds for both clinically relevant benefit and harm, indicating substantial uncertainty regarding the true treatment effect.
Eight patients from the intervention group (14.0%) and 10 controls (16.9%) died during follow-up (Table 1); however, differences between groups were not statistically significant (RR 0.80; 95% CI: 0.34–1.88). The incidence of high-risk MRPs was significantly higher among deceased patients of the intervention group, as compared to controls. Of the 26 high-risk MRPs, 34.6% were associated with inappropriate indication; 38.5% with dosing-related problems; 11.5% with drug–drug interactions; 7.7% with non-adherence; 3.8% with inadequate monitoring; and 3.8% with ADRs. A total of 88.5% of MRPs were resolved prior to death. According to the logistic regression model adjusted for hepatocarcinoma, each one-unit increase in the high-risk MRP rate was associated with a three-fold higher probability of mortality, regardless of the Child-Pugh score, MELD, and number of medications.10
Regarding medication discrepancies following reconciliation, a higher number of medications were associated with more discrepancies, including serious discrepancies that cause adverse events such as hepatic encephalopathy. Although baseline differences between groups were not observed, the pharmaceutical intervention resulted in a greater reduction in medication discrepancies in the intervention group, including total discrepancies, high-risk discrepancies, liver disease-related medication discrepancies, and other medication-related problems.6
A total of 375 potential MRPs were identified in the intervention group, with 221 (58.9%) having been resolved with the pharmaceutical intervention. At least one indication-related medication problem was identified in 47 patients (82.5%), with approximately one third considered high-risk. Adherence-related problems were detected in 38 patients (66.7%); supratherapeutic dosing in 31 patients, two-thirds of which were considered potentially associated with serious medication-related problems. Medication monitoring issues were observed in 30 patients; drug–drug interactions in 19 patients (87.5% severe), and 18 ADRs. High-risk MRPs were more likely to be resolved than low-risk ones. From unsolved MRPs, 12 patients died prior to resolution, although the cause of death was unrelated to medication.10 Multivariable analysis identified the intake of more than 10 medications, an age >55 years and a BMI <30 kg/m2 as independent predictors of high/very high-risk MRPs.8
DiscussionFollowing a literature search, a single study was selected for further analysis. The study reported no significant differences in terms of overall mortality or unadjusted risk of hospital admission. However, following adjustment for incidence rate, the pharmaceutical intervention was found to significantly reduce unplanned hospital admissions. The results of this clinical trial, however, should be interpreted with caution due to the limited sample size and the risk of bias.
These findings suggest that an increased rate of high-risk MRPs substantially augments the probability of death, regardless of the Child-Pugh score. A high proportion of medication-related hospital admissions in the control group were identified as avoidable.7 Accordingly, drug therapy monitoring emerges as a crucial approach to reducing risks and improving medication safety. These findings are consistent with other studies in LC patients reporting that dosing was inappropriate or the medication was contraindicated in 20% of cases. Additionally, evidence has been provided that 38% of patients develop an ADR, 70% of which were avoidable.12
A systematic review identified two studies evaluating the effectiveness of pharmaceutical interventions designed to reduce ADRs among patients with liver cirrhosis and liver transplant recipients. The interventions were primarily based on patient health education and therapeutic monitoring of immunosuppressive regimens. The two interventions were effective in reducing the absolute risk of clinical outcomes (adherence and percentage of time serum levels of immunosuppressants remained within range).1
Other systematic reviews in vulnerable polypharmacy patients reported inconsistent clinical outcomes of medication reviews. A systematic review identified a lack of robust evidence from studies conducted in older patients to conclusively demonstrate the impact of reducing inappropriate prescribing on hospital admissions, mortality, ADRs and quality of life. Nevertheless, the available findings suggest a potential beneficial effect of these interventions.13 A review revealed that medication reviews probably reduce hospital readmissions and visits to EDs, although no evidence was identified demonstrating changes in mortality or quality of life.14 Another systematic review found that outpatient medication management by a pharmacist and a physician in older adults was effective in reducing polypharmacy and improving treatment adherence; however, no evidence was provided of the impact of this intervention on clinical outcomes.15 A systematic review reported that medication review and deprescribing reduced hospital readmissions in older adults, primarily due to the reduction of unnecessary medication orders, with no differences observed in mortality.16
The robustness of our study lies in a thorough search based on a predefined PICO question, the implementation of a previously registered protocol, and compliance with PRISMA guidelines. The main limitation of this study is that we only identified a clinical trial assessing the impact of medication optimization on the safety of patients with LC, with a moderate risk of bias, primarily due to the limited size of the sample.
In conclusion, the only clinical trial included in our systematic review reported that drug therapy monitoring in outpatients with decompensated cirrhosis is effective in reducing unplanned medication-related hospital admissions and optimizing patient safety through the reduction of serious medication errors. Although a direct impact was not observed on overall mortality, the mere association between medication errors and the risk of mortality warrants the integration of pharmacists in multidisciplinary care teams. Further well-powered clinical trials are required to confirm these potential benefits and determine their effectiveness in routine clinical practice.
Ethical considerationsThe authors take full responsibility for the contents of this submission and meet ICMJE authorship criteria.
FundingNo funding was received for this work.
Authorship and copyright transferAndrea Rodríguez Esquíroz and Javier Garjón Parra contributed to the conception and design of the study, data collection, data analysis and data interpretation. Andrea Rodríguez Esquíroz drafted the manuscript. Javier Garjón Parra, Inés Aguinaga Ontoso, Amaya Echeverría Gorriti, Lorea Sanz Álvarez, and Marta Marín Marín performed a critical review of the manuscript. All authors approved the final version of the manuscript submitted for publication.
All authors assume full responsibility as defined by the International Committee of Medical Journal Editors.
Upon acceptance for publication, the authors hereby assign to the journal Hospital Pharmacy the exclusive rights to reproduce, distribute, translate, and publicly communicate the work in any medium or format, including print, audio, audiovisual, and electronic formats. To this end, a copyright assignment agreement will be signed at the time of submission through the online manuscript management system.
The authors confirm that there are no known conflicts of interest associated with this publication.

Supplementary material





